How do I tell if my HCG product is actually working?
Two subjective markers: increased testicular activity (the testes feel “fuller”, larger scrotal circumference) and returning morning erections. Objectively, a blood draw with testosterone, LH, FSH and estradiol two to three weeks into HCG use provides the reliable picture. If testosterone doesn’t rise or actually falls while HCG shots are running, that either points at an inactive product or at desensitisation.
Can HCG replace PCT?
No. HCG stimulates the testes but not the pituitary. After coming off HCG, the central system (hypothalamus, pituitary) stays suppressed unless a SERM is running in parallel. The established pattern: HCG in the last two to three weeks of the cycle to prime the testes, then a SERM (tamoxifen or clomiphene) in the PCT to reactivate central control.
How quickly does reconstituted HCG lose potency?
At 2–8°C in the fridge, protected from light, HCG stays biologically active for around 30 days. After four weeks the bioactivity drops measurably. Mixing a 5000-IU vial and using it across two months means the final week delivers noticeably less effective dose than the first. With Magnyl 5000, where the starting amount is already reduced, storage losses will push the effective dose toward zero.
Should I inject HCG intramuscularly or subcutaneously?
Both work. Subcutaneous is more practical (belly, fine insulin needle), IM is the classical route from the original registration trials. The pharmacokinetic difference is small — subcutaneous gives a slightly delayed but more even release. For the bodybuilding use case, subcutaneous is the practical standard.
What about HCG alternatives like kisspeptin or other peptides?
Kisspeptin-based approaches are experimental research, not a practical option. For a functioning cycle-plus-PCT the established route is SERM plus optional HCG in the transition. New peptides marketed as “a better alternative” usually have neither safety nor efficacy data in healthy users — the risk-benefit ratio is clearly worse than a correctly-dosed HCG from a licensed pharmacy.
What is the price of Magnyl at the steroid shop LabGain?
Steroid shop LabGain offers a wide selection of Magnyl in stock.
Buy Magnyl at prices ranging from 13 EUR to 20 EUR.
What other steroids for bodybuilding besides Magnyl are available for sale?
We offer a great selection of Oral and Injectable steroids, PCT, Fat burners, HGH and SARMs. We're sure that you find the best solution for your needs.
Magnyl by Magnus: an HCG product with a documented underdosing problem — and what that means for your protocol
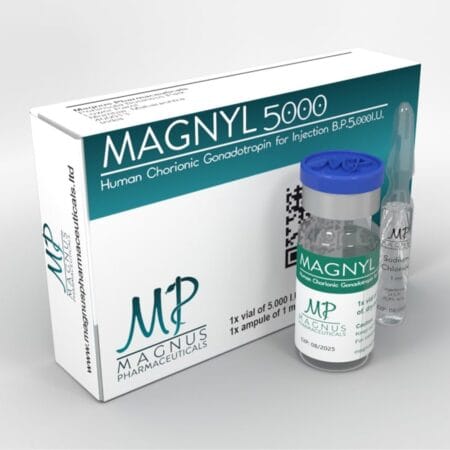
One independent lab test is enough to set this product apart from the pack. A Polish testing platform, kulturalnesuple.pl, ran an assay on a Magnyl 5000 vial and found only 1532 IU of actual HCG inside — against a declared 5000 IU on the label. That’s roughly 30.6% of what the box promises. Anyone buying Magnyl 5000 is getting about a third of what they’re paying for.
Before we get to the pharmacology of the substance itself: this quality story is the whole point. Everything else — mechanism, dosing, application profile — applies to any HCG product in the same class. What makes Magnyl 5000 specifically noteworthy is the gap between the label and the vial contents.
The active ingredient behind the label
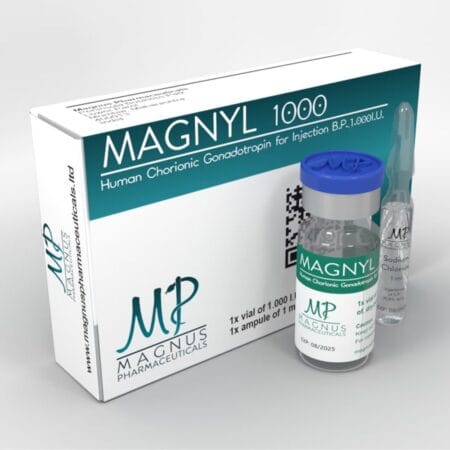
Magnyl (sometimes spelled Magnil in older listings) is produced by Magnus Pharmaceuticals. The vials contain, per label, either 1000 IU or 5000 IU of human chorionic gonadotropin as a lyophilised powder — a freeze-dried preparation that has to be reconstituted with sterile water before use.
HCG itself is a glycoprotein hormone made up of 244 amino acids, produced by the placenta during pregnancy. Clinical uses: luteal-phase support in reproductive medicine, cryptorchidism in adolescent males, delayed puberty, sometimes fertility therapy in men with hypogonadotropic hypogonadism. Prescription-only in Western markets, sold under names like Novarel, Pregnyl and Ovidrel (in the US), Choragon and Predalon (in Europe).
In bodybuilding, HCG serves one narrow purpose: keeping the testicles from shrinking during or after an anabolic cycle. It is not a muscle-building agent. It’s about holding Leydig-cell signalling active while the pituitary sits idle under exogenous testosterone.
The analysis, examined more closely
The kulturalnesuple.pl finding matters because it isn’t an outlier. The same platform ran a second UGL product — HCG 5000 by Luna Pharm, declared 5000 IU, measured 1021 IU — coming in at roughly 20% of the label claim. The pattern is consistent: UGL HCG is systematically underdosed.
The reason isn’t a mystery. HCG is a biological peptide hormone; its production, whether extracted from placenta or made recombinantly through CHO cell cultures, is expensive. A product with 5000 IU of actually present HCG has a raw-material cost that UGL pricing simply can’t cover at scale. What the user ends up with is either genuinely reduced active content, or a product that has lost part of its bioactivity through a broken cold chain in transit.
For the practical user: someone planning 500 IU every three days and reconstituting Magnyl 5000 is effectively delivering around 150 IU per shot. Compensating for it means dialing the dose up to about 1600 IU every three days — with the risk of tipping into an overdose the moment the next batch happens to be closer to spec.
What HCG does in the male body
HCG binds with high affinity to the LH receptor on the Leydig cells in the testes. Same receptor luteinising hormone uses — from the Leydig cell’s perspective, HCG looks nearly identical to LH. Activation → cholesterol uptake → StAR-protein transcription → testosterone synthesis → release into the bloodstream.
The effect stays limited to one leg of the axis. Central regulation via the hypothalamus and pituitary is untouched; if anything, the HCG-driven testosterone production reinforces the negative feedback and suppresses endogenous LH and FSH release further. HCG on its own does not restore the HPG axis — that job requires a SERM (tamoxifen, clomiphene).
One aspect that regularly gets missed: HCG-stimulated testosterone production in the testes also triggers more aromatisation. Estradiol can climb on an HCG run, with the well-known consequences — sensitive nipples, water retention, mood swings. A low-dose aromatase inhibitor during longer HCG use often makes sense.
How it actually gets used in practice
Goal
Dose
Frequency
Duration
Maintaining testicular activity on cycle
250–500 IU
2–3× per week
Cycle-long
End phase of a long cycle
500–1000 IU
Every 2 days
2–3 weeks
Kickstart before PCT
1000–2000 IU
Every 2 days
10–14 days
These numbers come from user reports and clinical use in secondary hypogonadism — not from trials in healthy athletes on supraphysiological testosterone. Reconstitution of a 5000-IU vial typically runs with 5 ml or 10 ml of bacteriostatic water. Five millilitres gives you 1000 IU per ml; ten gives you 500 IU per ml. Finer doses (250 IU) are perfectly doable with a 10-ml reconstitution and a 0.5-ml insulin syringe.
Storage: once reconstituted, HCG belongs in the fridge at 2–8°C. Use it inside two to four weeks. Over longer periods the peptide loses activity. Mixing a batch and using it across months compounds the effect on an already-underdosed product like Magnyl 5000 — the delivered dose approaches zero by the end.
Side effects and where it gets uncomfortable
The stimulated testosterone production in the testes brings its own effects, not identical to those of pure testosterone substitution:
Headaches, occasionally migraine-grade — common with the first shots
Irritability, mood swings
Redness and warmth at the injection site
With extended use: Leydig-cell desensitisation, with a fading testosterone response
Leydig-cell desensitisation is the pharmacological reason HCG can’t function as long-term therapy. After weeks of continuous LH-receptor activation the cells respond less; the testosterone answer to the same dose drops off. A two-to-four-week pause typically restores receptor sensitivity — hence the pulsed-cycle pattern in short bursts.
The quality issue with Magnyl 5000 amplifies the whole side-effect picture: someone who actually manages to deliver 500 IU (rather than the 150 IU the analysis suggests) risks an overshoot with stronger aromatisation, more pronounced headaches and heavier local reactions. Unpredictability is the real problem here.
Legal status
HCG is a prescription drug across Western markets. Legal supply runs through a pharmacy with a physician’s prescription — typical brand names are Novarel and Pregnyl in the US, Choragon and Predalon in Germany, Ovidrel elsewhere. Magnyl 5000 is not a licensed drug — it’s a grey-market product.
Criminal exposure for unprescribed possession sits at the misdemeanour level in most Western jurisdictions if the quantity is small; distribution and manufacture are handled more severely under drug-control legislation. Personal-use import through customs is inconsistently tolerated — HCG often gets treated as a “questionable medicine” with corresponding penalties.
On the WADA Prohibited List, HCG sits in category S2 (Peptide hormones, growth factors and related substances). For tested male athletes it is banned at all times — the rationale is the testosterone-stimulating effect that translates into indirect anabolic benefit. For female athletes the rule around HCG has traditionally been treated differently, since pregnancy is a natural cause of elevated HCG; current federation-specific application should be checked in each case.
Practical checks in real use
The legal route leads to a Western pharmacy. Anyone going grey-market should at minimum expect a cold-chain shipment, clean freeze-dried powder cakes without discolouration, and a legible batch number — and keep a reference sample from a licensed HCG vial handy for comparison. The one way to check your own vial at home is a bioassay or a standard pregnancy test (which reacts to HCG). A positive pregnancy test after reconstitution proves HCG is present — it doesn’t tell you how much. Quantitative confirmation requires a lab with an ELISA setup.
What we carry: Magnyl from Magnus in two ampoule sizes — 1000 IU and 5000 IU per vial, both as lyophilised powder. Other HCG products (Choragon, Predalon, Pregnyl) or alternative batches can be sourced on request. Given the analysis result described above for Magnyl 5000, checking the reactivity of your specific vial with a pregnancy-test strip before your first shot is a sensible precaution.