How do I know if my estradiol has dropped too low?
Dry joints, brittle skin, sinking libido, poor sleep, flat mood — those are the classic tells when an AI has been overdone. Bloods will confirm faster and more reliably than any self-check. Sensitive estradiol in the 20–40 pg/ml range is the target most male TRT users aim for.
How fast does anastrozole kick in?
Aromatase inhibition sets in within hours. Steady-state plasma levels take about seven days to build, which is why dose adjustments only show their full effect after a week. Subjective effects — less nipple sensitivity, less subcutaneous water — most users report over one to two weeks.
Does anastrozole help with deca or tren gyno?
No, and it can make things worse. Gyno under 19-nor compounds is largely progesterone- and prolactin-driven. Cabergoline, sometimes together with high-dose vitamin B6, is the right pharmacological angle. An AI here just pushes an already low E2 further down without touching the actual cause.
Can I pass a drug test on anastrozole if I get tested?
No. The parent compound and its metabolites are reliably picked up by LC-MS/MS. In the ITA cases, standard screening was enough to catch anastrozole in an athlete’s urine. A tested athlete taking an AI is squarely in the “deliberate rule violation” bucket, with the ban lengths that come with it.
Are the Teva and Mylan generics equivalent to Arimidex?
Generics approved in the US, EU and UK have to demonstrate bioequivalence to the reference product. The pharmacologically relevant parameters are comparable; the price gap comes from the patent expiration and manufacturing scale. What’s not equivalent is grey-market product of unknown origin — that stays questionable even when it wears a familiar manufacturer logo on the label.
What is the price of Anastrozol at the steroid shop LabGain?
Steroid shop LabGain offers a wide selection of Anastrozol in stock.
Buy Anastrozol at prices ranging from 0 EUR to 90 EUR.
What other steroids for bodybuilding besides Anastrozol are available for sale?
We offer a great selection of Oral and Injectable steroids, PCT, Fat burners, HGH and SARMs. We're sure that you find the best solution for your needs.
Anastrozole for men on cycle: what a third-generation aromatase inhibitor really does, sensible doses and where the risk sits
Anastrozole shows up in almost every English-language bodybuilding thread that touches on testosterone, trenbolone or boldenone. Usually shortened to “adex” or just “AI”. In the wider forum culture it is treated as a fix for puffy nipples and water weight; on the medicine side it is a third-generation aromatase inhibitor, developed by AstraZeneca and approved in 1995 as Arimidex for the adjuvant treatment of hormone-sensitive breast cancer in post-menopausal women. Prescription-only in the US, the EU and the UK. Anyone buying it outside of a prescription is buying it on the grey market, with everything that follows from that.
The debates around “nolva plus adex during PCT” or “adex for on-cycle E2 control” are older than most current lifters. What tends to be missing from those threads is the pharmacology and the hard numbers from the oncology trials — the same trials that decide how far you can push this molecule before the joints start protesting.
Chemistry, target and what AstraZeneca actually measured
Formally: C17H19N5, molecular weight 293.37 g/mol, CAS 120511-73-8. Anastrozole is a selective, non-steroidal aromatase inhibitor — unlike exemestane, which binds covalently and burns the enzyme out. Generic anastrozole is manufactured by Teva, Mylan, Accord, Sandoz and others; the reference product remains AstraZeneca’s Arimidex, dosed in 28- or 98-tablet blisters at 1 mg.
The oncology dose is 1 mg per day for roughly five years. Mechanism: anastrozole binds reversibly to the heme iron in the aromatase enzyme (cytochrome P450, CYP19A1) and blocks the conversion of androstenedione and testosterone into estrone and estradiol. In post-menopausal women, the pivotal trials showed serum estradiol dropping by about 80 percent. In men on TRT or anabolic cycle, the same reaction runs — only now it can slam estradiol down further than anyone wants, if the dose isn’t matched to the actual E2 reading.
One thing that sets anastrozole apart from older AIs like aminoglutethimide: it doesn’t touch cortisol or aldosterone synthesis. A whole class of legacy problems just vanishes. That’s most of the safety upside of the third generation.
Why the male-lifter data set is different from the oncology one
The registration trials ran on post-menopausal women. For men adding exogenous testosterone on top, there is zero controlled data with clinical endpoints. What circulates online as “the standard” — 0.5 mg twice a week for prevention, 1 mg per day for active sensitivity in the nipples — comes from user reports, not from prospective studies. Treat it accordingly.
Why lifters reach for it
Three use cases keep showing up in trip reports:
Gyno prevention during the cycle. Itchy, tender nipples are the early warning. Aromatisation of the exogenous testosterone lifts estradiol; that estradiol can push breast tissue toward fibrous growth. An AI intervenes right there — before the tissue crosses the point where only a scalpel fixes it.
Water retention and definition. Estrogen drives subcutaneous water. A lifter chasing a drier look on a testosterone or boldenone run will reach for an AI. The effect is real; it isn’t magic. Without a proper deficit and clean food, a low E2 does not produce contest condition on its own.
Add-on during PCT. After coming off an aromatising compound, the ratio of estrogen to testosterone can skew ugly. Anastrozole sometimes gets used here — remember though that tamoxifen (a SERM) addresses the central feedback loop through the pituitary, while anastrozole just dampens peripheral aromatisation. Two different tools for two different jobs.
A US-based reader on a classic test-E cycle described that 0.5 mg twice weekly kept his nipple sensitivity under control. That kind of anecdote proves nothing about causation and it is not a dosing prescription — it just shows how normalised that schedule is in practice.
Community doses, read with the appropriate skepticism
Situation
Amount
Frequency
Gyno prevention (light cycle)
0.25–0.5 mg
2× per week
Active gyno symptoms
0.5–1 mg
Daily until symptoms fade
PCT support
0.25–0.5 mg
1–2× per week
Half-life around 50 hours. Steady state after roughly one week. Time of day barely matters; consistency across the weeks does. Someone taking 1 mg today and 0.25 mg tomorrow just produces a wild hormone graph that harms more than it helps.
The rule that stuck in the community: as little as possible, as much as necessary. The reason is simple — E2 that gets pushed too low leaves men with joint pain, dry skin, killed libido and a mental fog nobody signs up for. Bloodwork beats gut feeling here, every time.
Side effects the oncology community already knows well
Anastrozole has its own side-effect profile that has nothing to do with anabolic use. The largest trial — ATAC, “Arimidex, Tamoxifen, Alone or in Combination” — enrolled more than 9,000 women and provides the most reliable frequency numbers we have:
Joint symptoms in 36% of patients (versus 29% on tamoxifen)
Cumulative fracture rate 15% (tamoxifen: 11%)
Rise in total cholesterol, with knock-on effects on cardiovascular risk
Hot flushes, nausea, fatigue, peripheral oedema, mood shifts
Those numbers come from post-menopausal women on breast cancer therapy under close medical supervision. For the 32-year-old powerlifter dosing his own test-cyp, no comparable numbers exist — the risks are known qualitatively, the exact magnitude isn’t.
One detail that regularly gets missed: for gynecomastia driven by 19-nor compounds (trenbolone, nandrolone, deca-durabolin), an AI doesn’t just fail to help — it often makes things worse. The trigger there is mostly progesterone- and prolactin-mediated. Cabergoline is the right pharmacological answer, sometimes stacked with high-dose vitamin B6.
Anastrozole vs. tamoxifen — not an either-or
The two get pitted against each other online, though they work on different problems. Anastrozole cuts estrogen production upstream; tamoxifen blocks estrogen receptors in breast tissue. Both are anti-estrogen, the attack points differ.
Anastrozole
Tamoxifen
Class
Aromatase inhibitor
SERM
Effect on systemic estradiol
Noticeably lowered
Essentially unchanged
For acute gyno
Useful as prevention
Stronger therapeutically
PCT capability
Supportive; doesn’t stimulate LH/FSH
Actively kicks the HPG axis
Headline risks
Bone density, cholesterol, joints
Thrombosis, IGF-1 suppression
Short version: for straight E2 control on cycle, anastrozole is the finer tool. For restarting your own testosterone production after the cycle, tamoxifen (or clomiphene) is pharmacologically the better bet.
Legal status and WADA position
Anastrozole is prescription-only in the US (FDA), the EU (EMA) and the UK (MHRA). Buying it without a prescription is illegal in each of those jurisdictions, as is possessing it with intent to distribute. Importing small quantities for personal use from an offshore pharmacy sits in a legal grey zone that varies country by country — customs services check for it regularly.
In organised sport the compound sits on the WADA Prohibited List, category S4.1 — “Aromatase inhibitors” — banned at all times, in and out of competition. The 2025 list explicitly classes anastrozole as a “specified substance”, which can matter for sanction sizing but doesn’t change the ban itself.
A recent case makes the point: the International Testing Agency (ITA) suspended a Kuwaiti ju-jitsu athlete for a positive result on drostanolone, 19-NA, anastrozole and tamoxifen — a multi-substance finding. Another case in the same discipline ended with a five-year ban for anastrozole alone.
On the grey-market quality side, the Polish customs analysis of 63 different PCT products from 2019 is worth knowing about: 34.9% of the samples contained none of the declared active ingredient. Of the rest, purity was inconsistent and 6.4% carried additional undeclared substances. Given the fake rate, blisters without a batch number, without a package insert, or with typos in the insert are the flags to watch for.
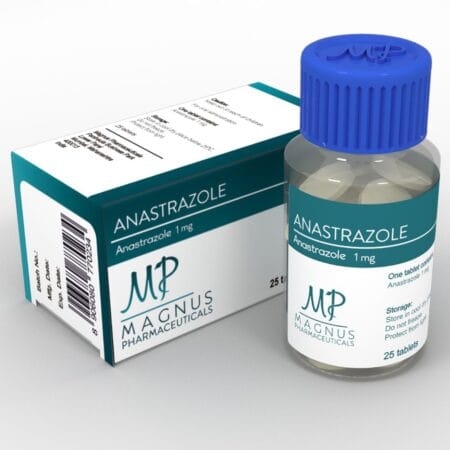
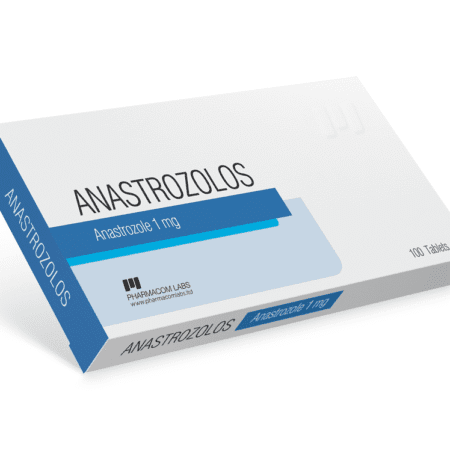
What we carry: anastrozole from Magnus in the classic 25-tab pack at 1 mg (the community workhorse), Prime’s 100-tab pack at 1 mg for longer runs, Pharmacom’s Anastrazolol 100-tab and Spectrum Pharma’s Arimidex via the USA-domestic supply route. Other manufacturers or pack sizes can be sourced on request — lead time depends on the specific supplier.